The pronator teres is easy to overlook. It’s a small, oblique muscle tucked into the proximal forearm, and it often hides behind a diagnosis of “golfer’s elbow,” “carpal tunnel,” or “nonspecific forearm pain.” When it’s involved, though, it can drive a surprising amount of medial elbow, volar forearm, and even median-distribution symptoms.
Quick Anatomy Refresher
Origin: Humeral head from the medial epicondyle of the humerus. Ulnar head from the coronoid process.
Insertion: Pronator tuberosity, mid-lateral shaft of the radius.
Innervation: Median nerve (C6–C7).
Action: Forearm pronation, with a minor assist to elbow flexion.
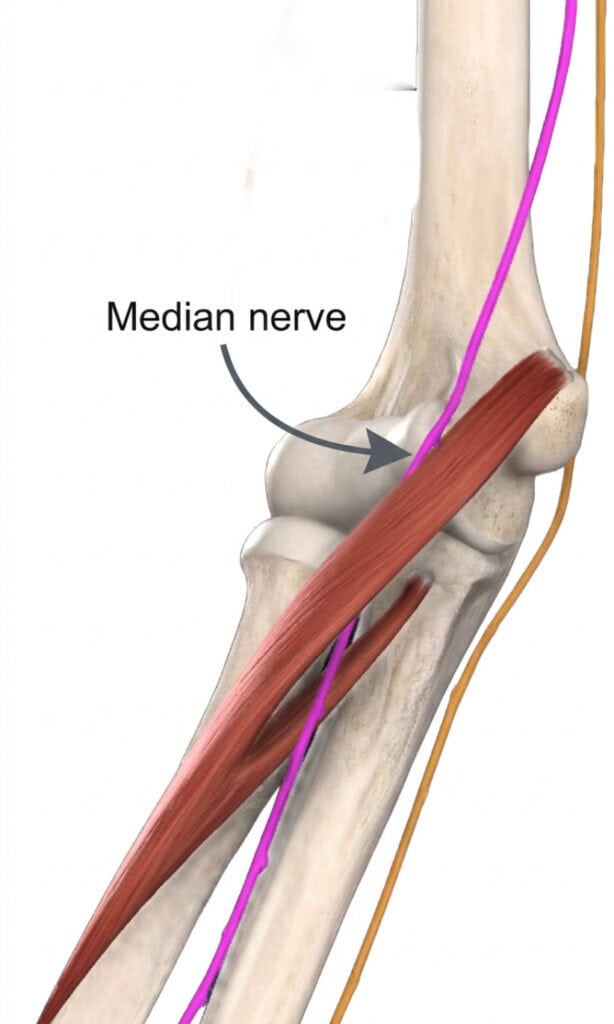
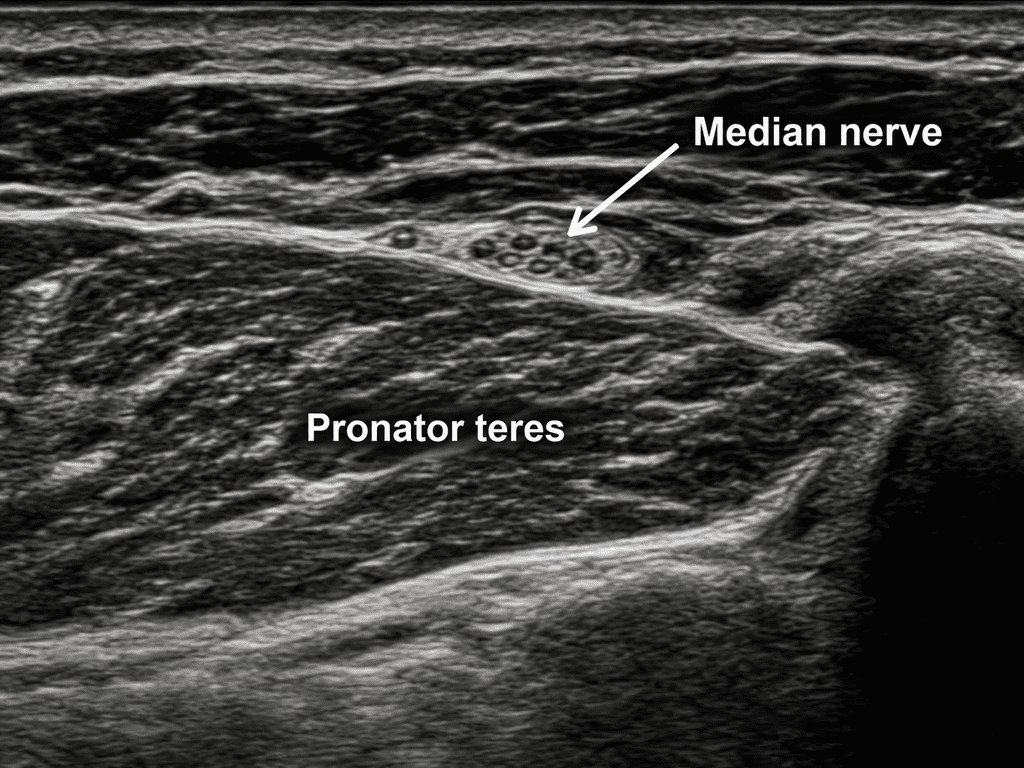
The key relationship: The median nerve typically passes between the two heads of the pronator teres
Pearl 1: Think Pronator Teres in Medial Elbow and Volar Forearm Pain
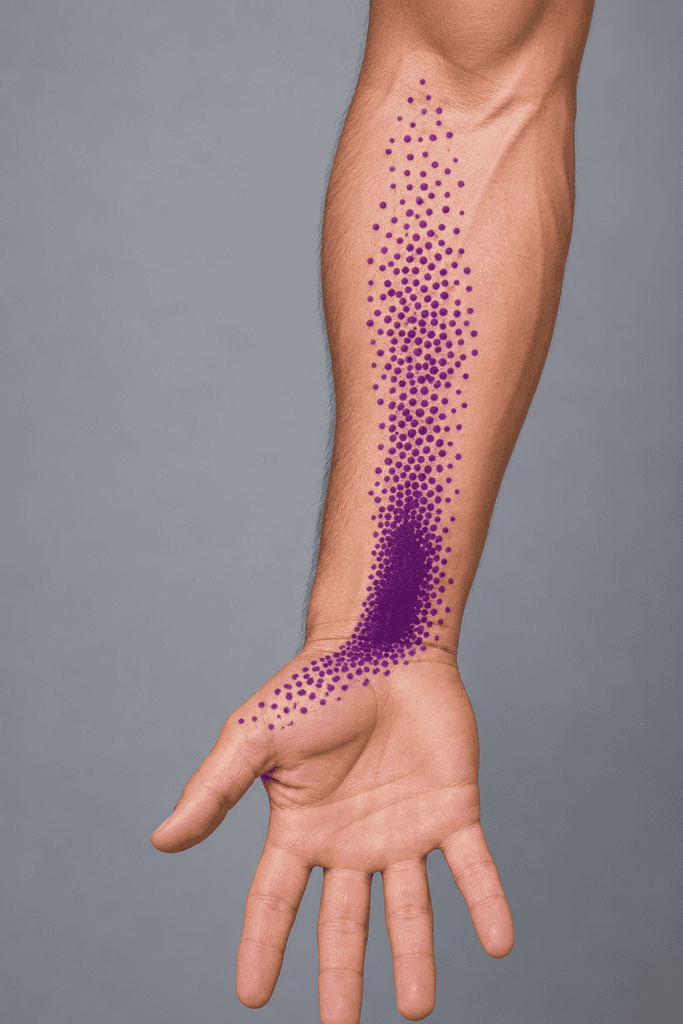
Myofascial trigger points in the pronator teres classically refer a deep, aching pain to the volar forearm and radial side of the wrist. If your patient with “medial elbow pain” has poor response to treatment at the common flexor tendon alone, look one step distal and lateral. The pronator teres belly is a frequently missed contributor.
Pearl 2: The Median Nerve Connection Changes Everything
A tight or hypertonic pronator teres can contribute to median nerve compression at the elbow (pronator syndrome).
Differentiating pronator syndrome from carpal tunnel syndrome:
The palmar cutaneous branch leaves the median nerve proximal to the carpal tunnel. In pronator syndrome, sensation over the thenar eminence may be altered. In carpal tunnel syndrome it’s typically spared.
Nocturnal symptoms are classic for carpal tunnel and less prominent in pronator syndrome.
Symptoms in pronator syndrome tend to be provoked by repetitive pronation or gripping.
Pearl 3: Treat the Contractile Tissue, Then Reassess the Nerve
Dry needling addresses the muscle, not the nerve directly. The rationale is that reducing hypertonicity and taut-band tension in the pronator teres may reduce the mechanical load on adjacent neural structures and improve pronation and supination range. Test your patient’s median nerve neurodynamics, resisted pronation, and grip before and after. If symptoms change after pronator teres treatment, you’ve learned something diagnostic as well as therapeutic.
Pearl 4: Look Upstream and Downstream
The pronator teres rarely acts alone. Consider these in your assessment:
Flexor-pronator mass: The pronator teres is part of the group that provides dynamic support to the medial elbow against valgus stress. This matters for throwers and racquet-sport athletes.
Repetitive pronation tasks: Keyboard and mouse use, tool use, and instrument playing are common culprits.
Cervical and thoracic contributors: C6–C7 radiculopathy and thoracic outlet involvement can mimic or coexist with PT-related symptoms (the “double crush” concept).
Take-Home Points
Suspect the pronator teres in medial elbow, volar forearm, and radial wrist pain, especially when common flexor tendon treatment stalls.
Consider pronator syndrome when carpal tunnel management isn’t working. Check thenar sensation and resisted pronation.
Needle with anatomical respect. The median nerve and brachial artery are close neighbors.
Reassess neurodynamics, pronation/supination, and grip after treatment. Let the response guide your clinical reasoning.
Pair needling with active care, since the goal is to change how the arm functions.
Want a refresher in dry needling the pronator teres?
Remember to look online for our scheduled Jam Sessions in Bethesda, MD.
Clinicians are eligible to be listed in the Find a Clinician directory when they complete one of the Myopain Seminars Course Certifications like the entire Dry Needling certification to become a CMTPT-Needling.
The Dry Needling Program (DN)
Certified Myofascial Trigger Point Therapist: CMTPT/DN
The Manual Trigger Point Therapy Program (MTT)
Certified Myofascial Trigger Point Therapist: CMTPT/MTT
The Dry Needling for Occupational Therapists Program (DNOT)
Certified Myofascial Trigger Point Therapist: CMTPT/DN
The Orofacial Dry Needling Program (ODN)
Certified in Orofacial Dry Needling: CMTPT/ODN
The Trigger Point Acupuncture Dry Needling Program
Certified in Trigger Point Acupuncture/Dry Needling: CMTPT/DNAc
Clinicians are also eligible to be included if they have completed:
The Fascial Manipulation® course program (FM 1-3) and passed the FM examinations
The CRAFTA course program (CRAFTA 1-3) and passed the CRAFTA certification examinations
Three of the Eureka Seminars / Myopain Seminars Pelvic Health courses – Pelvic Heath Certified (PHC)
The Functional Fascia Therapeutics (FFT) course (formerly known as Fu’s Subcutaneous Needling or FSN)
THANK YOU!
We’ve received your message and a member of the Myopain Seminars team will respond as soon as possible.
While you’re here, you may want to explore our upcoming courses and educational resources.